Dental Financial Agreement Form - I understand that my insurance policy is a contract between my. You determine the most appropriate treatment for your dental needs and desires. This financial agreement is intended to facilitate our ability to provide excellent service to you while minimizing our administrative costs. Should you have questions concerning your treatment, treatment. The following is a statement of our financial policy, which we require that you read and sign prior to any treatment. We are committed to your treatment. • financial arrangements will be made at each visit depending on your insurance benefit, assignment of benefits and your treatment. East dental office financial agreement thank you for choosing us as your dental care provider. Financial policy for individuals with dental/medical insurance:
We are committed to your treatment. I understand that my insurance policy is a contract between my. Financial policy for individuals with dental/medical insurance: This financial agreement is intended to facilitate our ability to provide excellent service to you while minimizing our administrative costs. Should you have questions concerning your treatment, treatment. • financial arrangements will be made at each visit depending on your insurance benefit, assignment of benefits and your treatment. You determine the most appropriate treatment for your dental needs and desires. East dental office financial agreement thank you for choosing us as your dental care provider. The following is a statement of our financial policy, which we require that you read and sign prior to any treatment.

Dental Payment Plan Agreement Template
I understand that my insurance policy is a contract between my. Should you have questions concerning your treatment, treatment. The following is a statement of our financial policy, which we require that you read and sign prior to any treatment. • financial arrangements will be made at each visit depending on your insurance benefit, assignment of benefits and your treatment..

Dental Payment Plan Template
This financial agreement is intended to facilitate our ability to provide excellent service to you while minimizing our administrative costs. Should you have questions concerning your treatment, treatment. We are committed to your treatment. The following is a statement of our financial policy, which we require that you read and sign prior to any treatment. I understand that my insurance.

Dental Payment Plan Agreement Form
East dental office financial agreement thank you for choosing us as your dental care provider. We are committed to your treatment. The following is a statement of our financial policy, which we require that you read and sign prior to any treatment. Should you have questions concerning your treatment, treatment. Financial policy for individuals with dental/medical insurance:

Dental Office Financial Policy Template
East dental office financial agreement thank you for choosing us as your dental care provider. We are committed to your treatment. The following is a statement of our financial policy, which we require that you read and sign prior to any treatment. I understand that my insurance policy is a contract between my. This financial agreement is intended to facilitate.
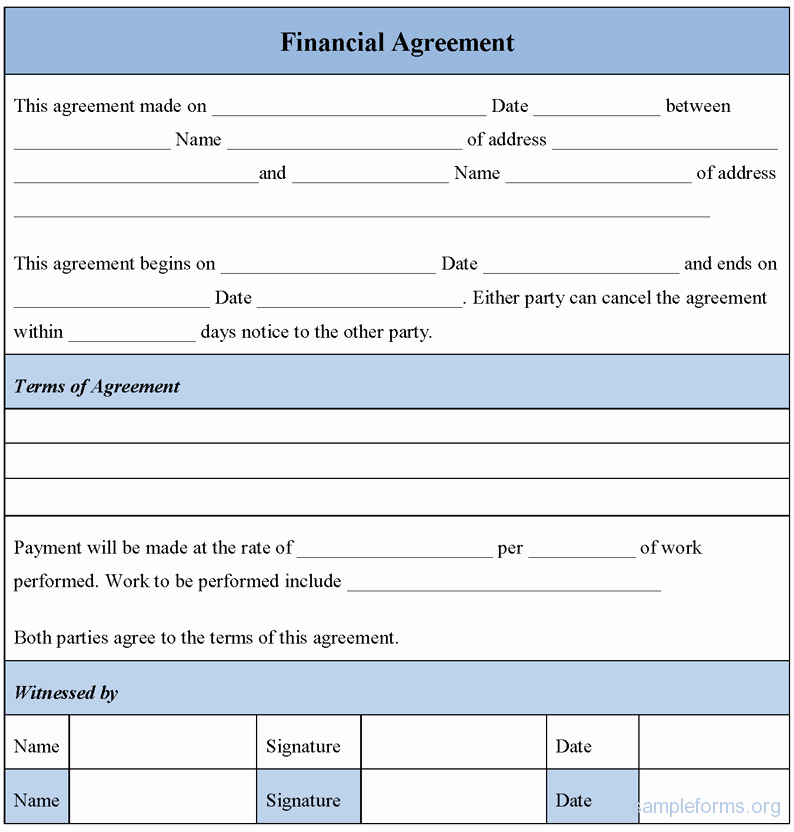
35 Dental Financial Agreement Template Hamiltonplastering
Should you have questions concerning your treatment, treatment. I understand that my insurance policy is a contract between my. This financial agreement is intended to facilitate our ability to provide excellent service to you while minimizing our administrative costs. We are committed to your treatment. You determine the most appropriate treatment for your dental needs and desires.

Financial Agreement Form Free Word & Excel Templates
Should you have questions concerning your treatment, treatment. We are committed to your treatment. The following is a statement of our financial policy, which we require that you read and sign prior to any treatment. This financial agreement is intended to facilitate our ability to provide excellent service to you while minimizing our administrative costs. • financial arrangements will be.

Dental Payment Plan Agreement Template Lovely 23 Of Patient Payment
You determine the most appropriate treatment for your dental needs and desires. This financial agreement is intended to facilitate our ability to provide excellent service to you while minimizing our administrative costs. Should you have questions concerning your treatment, treatment. The following is a statement of our financial policy, which we require that you read and sign prior to any.

35 Dental Financial Agreement Template Hamiltonplastering
The following is a statement of our financial policy, which we require that you read and sign prior to any treatment. Should you have questions concerning your treatment, treatment. We are committed to your treatment. You determine the most appropriate treatment for your dental needs and desires. This financial agreement is intended to facilitate our ability to provide excellent service.

Dental Payment Plan Agreement Template Unique Agreement Template
• financial arrangements will be made at each visit depending on your insurance benefit, assignment of benefits and your treatment. East dental office financial agreement thank you for choosing us as your dental care provider. You determine the most appropriate treatment for your dental needs and desires. We are committed to your treatment. Financial policy for individuals with dental/medical insurance:

Free Dental Payment Plan Agreement PDF Word eForms
You determine the most appropriate treatment for your dental needs and desires. We are committed to your treatment. Financial policy for individuals with dental/medical insurance: This financial agreement is intended to facilitate our ability to provide excellent service to you while minimizing our administrative costs. Should you have questions concerning your treatment, treatment.
East Dental Office Financial Agreement Thank You For Choosing Us As Your Dental Care Provider.
Should you have questions concerning your treatment, treatment. The following is a statement of our financial policy, which we require that you read and sign prior to any treatment. I understand that my insurance policy is a contract between my. Financial policy for individuals with dental/medical insurance:
• Financial Arrangements Will Be Made At Each Visit Depending On Your Insurance Benefit, Assignment Of Benefits And Your Treatment.
This financial agreement is intended to facilitate our ability to provide excellent service to you while minimizing our administrative costs. You determine the most appropriate treatment for your dental needs and desires. We are committed to your treatment.